What the Anion Gap Indicates
The gap calculation is a calculated value that assists clinicians in understanding acid-base status and identify hidden electrolyte disturbance. It is based on routine laboratory values from a blood test and reflects the disparity between measured positively charged ions and negatively charged ions in the blood.
In https://anion-gap-tracker244.cavandoragh.org/what-does-low-bicarbonate-along-with-a-high-anion-gap-mean practice, the calculation uses sodium levels, serum chloride, and bicarbonate, with serum potassium sometimes included depending on the formula. The result helps identify unmeasured negatively charged ions that may be accumulating during illness. Because of that, the anion gap is a useful clinical tool for evaluating an acidotic picture and narrowing the causes of acid buildup.
Most clinicians first review a standard metabolic panel or a blood gas analysis when acid-base problems are suspected. The anion gap can then help determine whether the patient has increased anion gap metabolic acidosis or regular anion gap metabolic acidosis. That distinction matters because the underlying causes, severity, and next steps can be very different.
Although the calculation is simple, the interpretation is not. The value is only one piece of the broader clinical assessment of the patient’s condition. It should be considered alongside symptoms, medications, kidney function, glucose, lactate, ketones, and other laboratory values.
How to Operate an Anion Gap Calculator
An anion gap calculator streamlines the gap calculation so you can rapidly read the result from a blood chemistry panel. To use it, enter the serum sodium, chloride, and bicarbonate values. Some calculators also let you add albumin and potassium, which enhances accuracy in certain cases.
The main advantage of a calculator is speed and consistency. It cuts down on arithmetic mistakes and helps organize the evaluation of metabolic derangement. In many cases, the calculator will also display a corrected result if the serum albumin is low, since hypoalbuminemia can reduce the apparent gap and obscure clinically important disease.
A practical workflow looks like this:
- Review the basic metabolic panel or blood gas. Enter serum sodium, serum chloride, and bicarbonate. Include albumin if the calculator supports albumin correction. Check the calculated anion gap against the expected reference interval. If the gap is elevated, evaluate causes of metabolic acidosis. If the result is abnormal, consider whether a mixed acid-base disorder is present.
The calculator is most helpful when paired with the rest of the acid-base picture. A normal number does not automatically mean normal physiology, and an elevated number does not identify the cause by itself. It is a guide for further clinical interpretation, not a final diagnosis.
Formula for Anion Gap & Reference Ranges
The standard anion gap formula reads:
Anion gap = sodium - (chloride + bicarbonate)
Some clinicians add potassium in the formula, but many updated calculators exclude it because the impact is small. When potassium is included, the result is slightly higher, but the same overall interpretive principles apply.
The normal anion gap is based on the lab method and the reference range provided by the laboratory. Different analyzers and measurement techniques can change the expected interval. That is why it is best to interpret the result using the lab’s own reference interval rather than a universal cutoff alone.
Albumin correction is important because serum albumin is a major unmeasured anion. When albumin is low, the anion gap may appear falsely normal. Correcting for albumin helps reveal a hidden increase in unmeasured anions. This can be especially important in critically ill patients with metabolic acidosis.
A common clinical approach is to adjust the gap upward when albumin is below normal. The exact correction factor can change by method, but the principle is the same: low albumin lowers the measured anion difference, so correction improves accuracy. For that reason, a good anion gap calculator often offers albumin correction as a built-in feature.
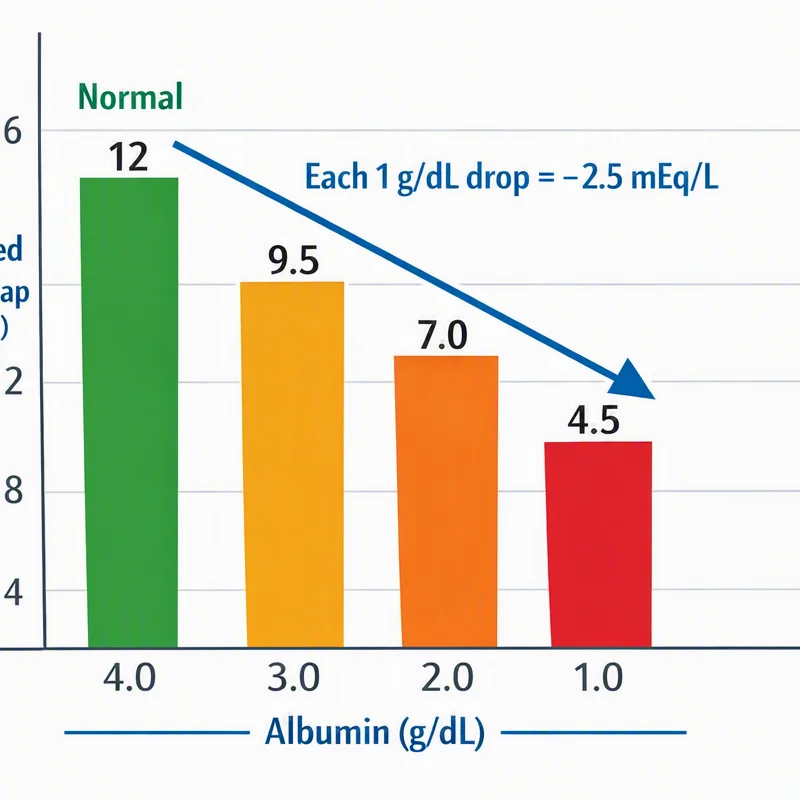
Understanding the formula also helps clarify the physiology. The serum contains measured cations and anions, but not all ions are directly measured. The gap represents the difference created by these unmeasured anions, making it a helpful window into hidden metabolic processes.
What exactly the Delta Gap Is and Why It Matters
The delta gap extends the reading of the anion gap by weighing the increase in gap to the fall in bicarbonate. This comparison helps determine whether the patient has only one acid-base problem or a mixed acid-base disorder. It is especially useful in metabolic acidosis when the clinician wants to know if another process is also changing the bicarbonate level.
This is where the delta-delta ratio is used. The ratio measures the change in anion gap to the change in bicarbonate. If the ratio shows a mismatch, it may point to an additional disorder such as metabolic alkalosis or another type of metabolic derangement occurring at the same time.
Why does this matter? Because not all cases of acidosis are clear-cut. A patient with high anion gap metabolic acidosis may also have vomiting, diuretic use, or other factors that shift bicarbonate in the opposite direction. The delta gap and delta-delta ratio help expose those overlapping patterns.
In short, the delta gap is a delta calculation that enhances the initial gap calculation. Instead of asking only whether the anion gap is elevated, it asks whether the increase in gap matches the expected drop in bicarbonate. That makes it an valuable tool for acid-base interpretation.
Sequential Delta Gap Calculation
To determine the delta gap, at first determine the measured anion gap from the chemistry values. Afterward compare it to the expected anion gap, which is often the upper end of the lab’s normal reference interval. The difference between the measured and expected values is the delta.
Then, compare that delta with the drop in bicarbonate. This comparison can help assess whether the bicarbonate loss is proportional to the increase in unmeasured acids.
A basic approach looks like this:
- Determine the measured anion gap. Identify the expected anion gap from the lab reference range. Subtract expected from measured to find the delta gap. Match that value with the change in bicarbonate. Interpret the pattern using the delta-delta ratio.
If the rise in anion gap is larger than the fall in bicarbonate, a second process such as metabolic alkalosis or preexisting elevated bicarbonate may be present. If bicarbonate falls more than expected, another acidifying process may be contributing. Either way, the result supports more nuanced acid-base interpretation.
This systematic approach is particularly useful when the clinical picture is unclear. For example, a patient may have metabolic acidosis from one source and vomiting-related alkalosis from another. A basic gap calculation alone may miss that combination, but the delta gap can point toward a mixed acid-base disorder.
How to Read Usual Results
A increased anion gap metabolic acidosis often indicates there is excess of acidic compounds or other unaccounted anions. The most common clinical question is not simply if the gap is increased, but what is driving the rise and whether compensation is appropriate.
In contrast, normal anion gap metabolic acidosis indicates that bicarbonate has been removed and substituted with chloride, so the gap stays within the reference interval. This pattern is commonly termed hyperchloremic acidosis because chloride rises as bicarbonate drops.
Respiratory compensation should also be checked. In metabolic acidosis, the body generally boosts ventilation to lower carbon dioxide and partially correct pH. A blood gas can help determine whether the compensatory response is appropriate or whether another respiratory disorder is present.
Frequent clinical patterns include:
- Elevated anion gap metabolic acidosis with appropriate respiratory compensation. Normal-gap metabolic acidosis with elevated chloride and bicarbonate loss. Metabolic acidosis with a superimposed mixed acid-base disorder. Elevated gap with unexpected bicarbonate behavior suggesting a second process.
In practice, clinicians use the anion gap, delta gap, and blood gas in combination. The pattern is more significant than any single number. A patient can look medically stable while having a substantial underlying metabolic problem, or appear quite ill with only minor changes in the measured gap.
Reasons of Raised Anion Gap
A expanded anion gap suggests accumulation of unmeasured anions. Various major conditions can lead to this pattern, and the differential diagnosis depends on the general clinical picture, medications, and other lab findings.
Lactic acidosis is a common cause and may occur with tissue hypoperfusion, sepsis, seizures, or severe illness. Elevated lactate introduces unmeasured acid to the blood and often causes high anion gap metabolic acidosis.
Diabetic ketoacidosis is an additional classic cause. Ketone bodies build up and lower bicarbonate while increasing the gap. This is a key example of metabolic derangement where the anion gap calculator can rapidly highlight the severity of the acid-base problem.
Renal failure can also elevate the anion gap because the kidneys cannot excrete acid properly. Retained acids and reduced clearance of metabolic byproducts can add to the acidotic state.
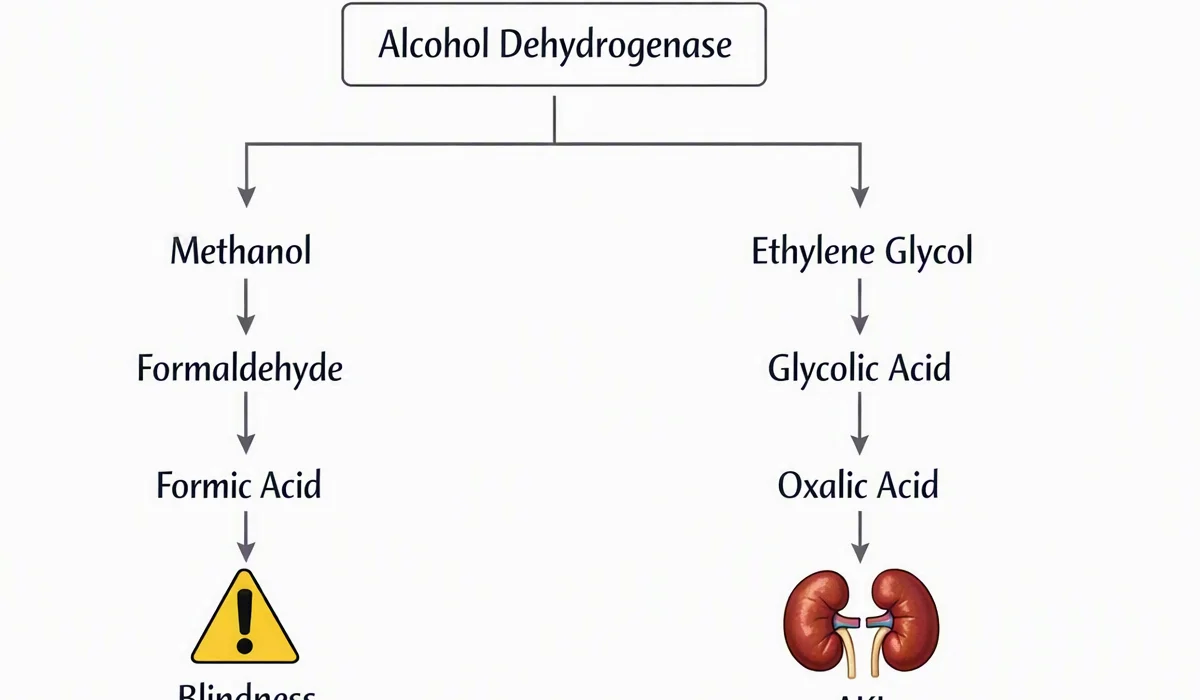
Toxic alcohols are an important and potentially dangerous cause. Methanol, ethylene glycol, and similar substances can generate acidic metabolites that elevate the gap. In these cases, the gap may be only one clue among many, and urgent clinical assessment is essential.
Other causes may include medications, toxins, and inborn metabolic problems, but the major categories above are the most commonly emphasized. The key point is that an elevated anion gap signals a need to look for hidden acids, not simply to treat the number itself.
Causes of Regular Anion Gap Metabolic Acidosis
Regular anion gap metabolic acidosis usually reflects direct loss of bicarbonate rather than increase of unidentified acids. Since the lost bicarbonate is replaced by chloride, the serum chloride tends to increase, producing hyperchloremia.
Diarrhea is a classic cause because the gastrointestinal tract can shed large amounts of bicarbonate-rich fluid. This causes metabolic acidosis with a normal gap and elevated chloride.
Renal tubular acidosis is another significant cause. In this condition, the kidneys fail to handle acid and bicarbonate properly, causing persistent acid-base imbalance. Different forms of renal tubular acidosis can have different mechanisms, but they share the pattern of normal gap acidosis.
Bicarbonate loss can also occur through fistulas, certain medications, or renal causes. The common theme is that bicarbonate declines without a corresponding rise in unmeasured anions, so the anion gap may persist within range.
These patterns matter because they change the workup. If the anion gap is normal, the next question is often whether the problem is gastrointestinal loss, renal tubular disease, or another cause of bicarbonate loss. The chloride level and blood gas results are especially helpful in that analysis.
Caveats and Clinical Caveats
Even a well-designed anion gap calculator has limitations. The biggest one is albumin correction. Because albumin is a key unmeasured anion, low serum levels can conceal a true elevation in the gap. Without adjustment, a significant disorder may be missed.
Lab error is another caveat. Sample contamination, analyzer variation, or transcription mistakes can distort the result. If the value does not fit the clinical picture, repeat testing and review of the original basic metabolic panel may be necessary.
The computed result also indicates the overall acid-base balance at a single moment. It does not indicate how quickly the disorder developed or whether the patient is improving. Serial results can be more informative than a single measurement.
Lastly, clinical context is essential. A mildly abnormal anion gap in a stable patient has a different meaning than the same result in someone with shock, altered mental status, or kidney injury. The calculator supports judgment, but it does not replace it.
For best results, evaluate the anion gap, delta gap, and blood gas together, then compare them with symptoms, medications, and the rest of the chemistry profile. That holistic approach improves the chance of identifying mixed acid-base disorder and determining the right underlying cause.
FAQ About Anion Gap and Delta Gap Calculators
What is an anion gap calculator used for?
An anion gap calculator is used to rapidly assess metabolic acidosis and identify whether the problem is likely to be a high anion gap metabolic acidosis or a normal anion gap metabolic acidosis. It helps clinicians read electrolyte patterns from lab values and decide whether further evaluation is needed.
How is the delta gap calculated?
To calculate the delta gap, first find the measured anion gap, then compare it with the expected anion gap from the lab’s reference interval. The difference is compared with the drop in bicarbonate. This helps determine whether there may be a mixed acid-base disorder.
Why can albumin affect the anion gap?
Albumin is a major unmeasured anion, so lower albumin reduces the apparent anion gap. That is why albumin correction matters. Without it, a true gap elevation may be missed, especially in patients with significant illness or low serum albumin.
What is the meaning of a high anion gap mean?
A high anion gap often means there are additional unmeasured acid substances in the blood, such as those seen in lactic acidosis, diabetic ketoacidosis, renal failure, or toxic alcohols. It typically suggests metabolic acidosis and should be assessed with the blood gas and overall clinical picture.
Can a normal anion gap still indicate metabolic acidosis?
Absolutely. Normal anion gap metabolic acidosis is frequent and often results from diarrhea, renal tubular acidosis, or other causes of bicarbonate loss. In this case, chloride often rises to maintain electroneutrality, so the gap may remain normal even though the patient is acidotic.