What the Anion Gap Shows
The anion gap is a practical way to interpret electrolytes from a serum chemistry panel and estimate the amount of unmeasured anions in the blood. It assists clinicians check acid-base balance and spot patterns that may point to a metabolic disorder. An elevated or reduced result does not diagnose a disease on its own, but it gives important clues that guide clinical interpretation.
An anion gap calculator is a useful diagnostic tool because it turns common lab values into a informative number. The calculation uses the major measured ions in an electrolyte panel to determine whether there is an excess of acids, a deficiency of proteins, or another variation affecting the body’s chemistry. In routine practice, it is usually used to investigate metabolic acidosis and distinguish between different causes of a disturbed acid-base state.
Most of the time, the gap shows the balance between positive ions and negatively charged ions. Because some important ions are not directly measured on standard blood test results, the result helps reveal hidden changes in the blood. That is why the anion gap is so useful for diagnosis support, especially when symptoms are nonspecific and the blood test results need a careful look.
Anion Gap Formula and Inputs
The main anion gap formula is based on three common lab values: sodium, chloride, and bicarbonate. In its simplest form, the formula is:
Anion gap = sodium - (chloride + bicarbonate)
These values are typically taken from a serum chemistry panel. More specifically, you may see serum sodium, serum chloride, and serum bicarbonate shown in the report. Because these are standard components of the chemistry panel, the calculation can be done rapidly with the help of an anion gap calculator or without a calculator for review.
Some laboratories may use slightly different methods or reporting conventions. Some include potassium in the formula, while others do not. For everyday use, the sodium-based version is the most common. What matters most is that you use the same method as the lab reference range or reference interval included in the report, since that affects how the result is interpreted.
To calculate anion gap accurately, ensure the input values come from the same sample and the same time point. Mixed or outdated lab values can produce a misleading number. This is especially important when monitoring a evolving acid-base disorder or following treatment for a metabolic acidosis.
How to Operate an Anion Gap Calculator
A calculator for the anion gap is simple to use, but the nuances matter. A systematic calculation helps reduce mistakes and makes the result easier to interpret in context. Start with the sodium value, then subtract the sum of chloride and bicarbonate. The number you get is the estimated amount of unmeasured anions.
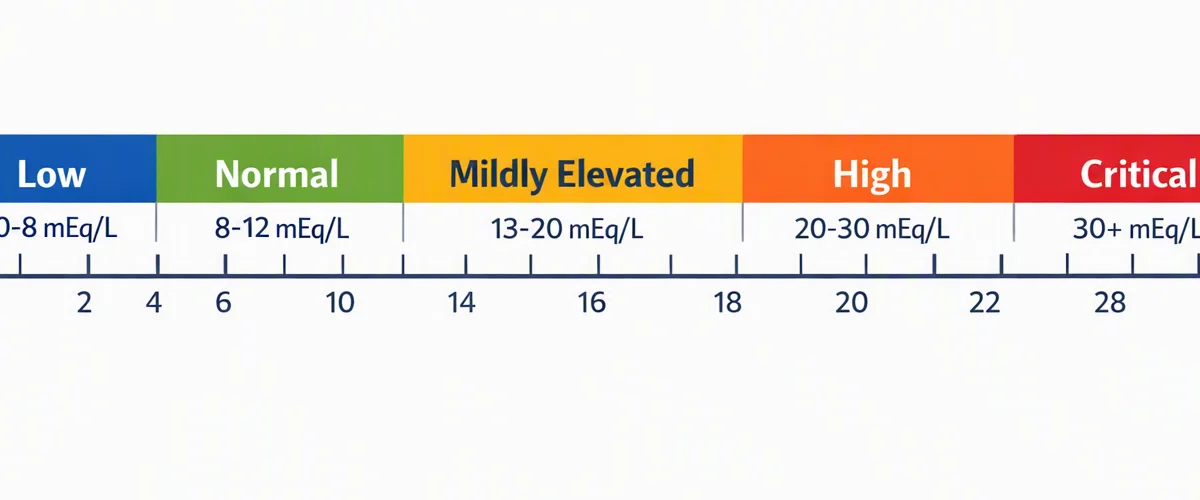
Here is a simple approach:
- Locate the serum sodium value from the electrolyte panel. Identify the serum chloride value. Locate the serum bicarbonate value. Combine chloride and bicarbonate together. Take away that total from sodium.
This step-by-step calculation is the same process used by many online and clinical medical calculator tools. The main plus of a calculator is speed, but the real value comes from understanding what the number means once you have it.
Consistently compare the result with the lab’s reference range. A number that seems mildly off in one setting may be expected in another, depending on the laboratory method and whether the patient has low albumin. Good clinical interpretation requires both the result and the clinical story.

Typical vs Increased Anion Gap
A normal gap suggests that the equilibrium between measured positive ions and measured negative ions is in the expected range. A increased anion gap indicates that extra acid substances are likely present, which often points toward a form of high anion gap metabolic acidosis.
In contrast, a normal result does not always mean everything is fine. Some patients with normal anion gap metabolic acidosis may still show a important acid-base disturbance, often due to bicarbonate loss or chloride retention. This is why test interpretation should always consider the full profile of electrolytes, not the gap alone.
A high gap is especially helpful for identifying hidden acid accumulation. In metabolic acidosis, the anion gap can point toward causes such as lactate buildup, ketones, kidney dysfunction, or certain toxins. A normal gap can instead point to a different metabolic process that needs an alternate diagnostic pathway.
The key point is that the anion gap is a recognition tool. It assists the clinician by showing whether the blood chemistry fits a high gap or low gap pattern, and that can sharpen the list of possible causes rapidly.
Typical Causes of a High Anion Gap
A high anion gap metabolic acidosis occurs when acids accumulate in the blood and add extra unmeasured anions. Several common conditions can do this, and the clinical context usually helps distinguish among them.
Lactic acidosis is one of the most typical causes. It can occur when tissues are not obtaining enough oxygen, when severe infection is present, or when metabolism is otherwise under strain. In this setting, lactate increases and the gap rises.
Ketoacidosis is another major cause. It can develop when the body breaks down fat for fuel and produces ketone acids. This pattern is often seen with uncontrolled diabetes, prolonged fasting, or heavy alcohol use. The exact cause depends on the overall presentation, but the anion gap often becomes clearly elevated.
Reduced kidney function can also cause a high gap because the kidneys are less able to clear acids from the body. As acid retention increases, the gap may rise progressively. This makes the anion gap a useful marker when evaluating kidney-related metabolic changes.
Toxins are another important category. Certain ingestions and exposures can produce an elevated gap by introducing acids or toxic metabolites. Salicylates are a classic example and should be considered when the lab pattern and symptoms fit. Because toxin-related causes can be serious, an unexpected high gap should prompt careful review of medication history, exposures, and accompanying symptoms.
Reduced Anion Gap Causes and Medical Significance
A low anion gap is less common than a high one, but it still is important. Often, the starting point is to consider lab error or a specimen issue, because inaccurate measurements are one of the most common explanations. Retesting can clarify whether the abnormality is real.
Hypoalbuminemia is a key true cause of a low gap. Albumin is a anionic protein, so when its level falls, the calculated gap may also fall. This is one reason the measured number can miss the real acid load if albumin is not considered.
Multiple myeloma is another significant cause because abnormal proteins in the blood can affect the distribution of charged particles. In some patients, this changes the anion gap to a degree to be noticeable on routine chemistry testing. A low result does not confirm the diagnosis, but it may provide a signal that prompts further evaluation.
Other causes include changes in measured ions or interference from unusual substances. The practical message is that a low gap should not be ignored. It may reflect lab error, low protein states, or a condition that requires more workup. If the value is unexpected, repeat testing and broader clinical assessment are often appropriate.
Albumin Correction and Corrected Anion Gap
Since albumin is a key unmeasured anion, it substantially affects the calculation. This is why an anion gap calculator is more accurate when it includes albumin correction or when the clinician corrects the result manually. The corrected anion gap aids estimate the actual acid-base picture when albumin is low.
The basis for this reference correction is simple: low albumin reduces the measured gap even if substantial acids are present. If it is not adjusted, the result may appear normal when it is not. That can obscure high anion gap metabolic acidosis and slow recognition of the real problem.
Albumin correction is a form of clinical interpretation that enhances accuracy. It is especially relevant in patients with chronic illness, inflammation, malnutrition, or liver-related changes in protein levels. In these settings, the uncorrected number can be inaccurate.
Various clinicians and laboratories may apply slightly different correction factors, so the main principle is to note that low albumin lowers the gap. If albumin is abnormal, a corrected value gives improved diagnosis support than the raw result alone.
In What Way Does Anion Gap Fits into Acid-Base Disorders
This anion gap is an element of the broader assessment of an acid-base disorder. It is especially useful in metabolic acidosis, where it helps differentiate high gap from normal gap patterns. This difference changes the differential diagnosis and the next steps in evaluation.
Respiratory compensation is part of the body’s response to metabolic acid buildup. When acidosis is present, breathing may become faster or deeper to help lower carbon dioxide and partially offset the pH change. The anion gap does not measure compensation directly, but it helps identify the primary metabolic problem that triggers it.
The delta gap is a further useful concept. It compares the change in the anion gap to the change in bicarbonate and helps reveal mixed disorders. For example, a patient may have a high gap acidosis plus another hidden metabolic issue at the same time. That is why the gap should be interpreted with the bicarbonate level, pH when available, and the overall electrolyte pattern.
In practice, the anion gap works best as a diagnostic tool. It does not replace full evaluation, but it gives structure to the analysis of acid-base balance and helps identify whether the pattern is more consistent with acid gain, bicarbonate loss, or a combined disturbance.
Frequently Asked Questions About Anion Gap Calculation
How is anion gap calculated from lab values?
Use the anion gap formula: sodium minus the sum of chloride and bicarbonate. In other words, take serum sodium and subtract serum chloride plus serum bicarbonate. An anion gap calculator can do this automatically, but the manual step-by-step calculation is easy to follow and helps with lab interpretation.
What is a normal anion gap range?
The lab reference range depends on the testing method used by the laboratory, so the exact reference interval can vary. In general, a result within the lab’s stated range is considered a normal anion gap. Always interpret the number using the specific report rather than assuming a universal cutoff.
Why is albumin used to correct the anion gap?
Albumin contains a minus charge and is a major undetected anion. When albumin is low, the observed gap can seem falsely low even if acid is present. Albumin correction offers a more accurate corrected anion gap and supports clinical interpretation, especially when assessing metabolic acidosis.
What does a high anion gap mean?
A high anion gap usually suggests extra acids or unmeasured anions in the blood. Frequent causes include lactic acid buildup, ketone-related acidosis, kidney failure, and specific toxins, including salicylates. It is a sign that often raises concern for high anion gap metabolic acidosis.
Can a low anion gap indicate a serious condition?
Certainly. A low anion gap can reflect hypoalbuminemia, myeloma, or at times lab error. Though it may be less urgent than a significantly elevated gap, it can still point to an important condition and should be reviewed in context with other laboratory results and the overall clinical picture.
When to Seek Medical Evaluation
Variations in the anion gap https://anion-gap-estimator556.huicopper.com/anion-gap-calculator-expected-range-and-interpretation should consistently be interpreted alongside symptoms and the full set of laboratory findings. If a person has signs of severe illness, confusion, rapid breathing, dehydration, persistent vomiting, chest pain, or worsening weakness, they may need prompt medical attention. Those symptoms can occur with severe acid-base problems and should not be ignored.
Important lab values deserve immediate evaluation, especially when the findings suggest significant acid buildup, kidney dysfunction, or poisoning. A worrisome result on the chemistry panel should lead to a prompt medical evaluation instead of delaying for symptoms to progress.
The anion gap is a valuable assessment and interpretation aid, but it is not a sole diagnostic. If you're using an anion gap calculator and the result looks off, the safest next step is to talk over the findings with a trained clinician. That is especially true when the result is paired with low or high bicarbonate, kidney issues, possible ingestion, or signs of metabolic acidosis.