What Is a Mixed Acid–Base Disorder?
A complex acid-base disorder occurs when multiple mechanism is affecting acid-base balance at the same moment. Instead of having a one clean pattern, the blood shows evidence of two or more overlapping abnormalities. This is important because a patient may seem acidotic, alkalotic, or even nearly normal on paper while still having a significant underlying problem.
The typical pairings involve metabolic acidosis along with a different process such as respiratory alkalosis. Clinically, this means one condition is decreasing bicarbonate or increasing acid load, while another is reducing carbon dioxide through overbreathing. The outcome can be puzzling unless you use a systematic clinical approach and evaluate the full clinical picture.
A mixed acid-base disturbance is not just a laboratory curiosity. It often reflects a major metabolic disturbance, ventilatory compensation that is overactive or inadequate, or an independent problem affecting the lungs and kidneys at the same time. Because of that, laboratory interpretation should always include serum chemistry, blood gas analysis, and the clinical context.
What Can an Elevated Anion Gap Signify?
The anion gap is a computed value used to detect abnormalities in electrolytes and acid-base status. It shows the difference between measured cations and measured anions in the serum, and it gives a clue about the presence of unmeasured anions in the bloodstream. When the elevated anion gap is present, it usually suggests that extra acids are accumulating.
An increased anion gap is most closely connected with high anion gap metabolic acidosis. In this scenario, bicarbonate is used up while acids rise, leaving behind negatively charged byproducts that are not directly measured on a standard panel. These may come from lactic acid, ketones, toxins, or impaired renal function.
Understanding the anion gap helps narrow the differential diagnosis. It does not tell you the exact cause by itself, but it often indicates that the body is dealing with a specific type of acid loading or loss of acid excretion. That is why the anion gap is such a helpful part of laboratory interpretation.
How the Anion Gap Calculator Helps Interpretation
An Anion Gap Calculator streamlines the anion gap formula more straightforward to apply and reduces mistakes during fast assessment. The calculation typically uses serum sodium, serum chloride, and serum bicarbonate. Because these values are often already available on a standard metabolic panel, the calculator turns raw serum chemistry into a more relevant result.
The classic formula is: sodium minus the sum of chloride and bicarbonate. That calculated value is the anion gap. A higher number supports the presence of extra unmeasured anions and may indicate a high anion gap metabolic acidosis. The calculator can also help you spot whether the pattern matches a single disorder or points to a mixed acid-base disorder.
Using an Anion Gap Calculator is valuable because the result alone is not enough. You still need to compare it with the blood gas, the pH, the pCO2, and the patient’s symptoms. In other words, the calculator aids clinical reasoning, but it does not replace it. The best use is as part of a broader diagnostic approach that includes compensation analysis and an underlying cause review.
Typical Causes of Mixed Acid-Base Imbalances With Increased Anion Gap
Several conditions can lead to a mixed acid-base imbalance with an elevated anion gap. Among the most common are lactic acidosis, ketoacidosis, and renal failure. Every one can produce a high-gap metabolic acidosis, and each can also overlap with another disorder such as alkalosis from breathing changes or respiratory compensation that is more pronounced than expected.
Lactic acidosis develops when tissues are deprived of adequate oxygen or when cells cannot use oxygen normally. The consequence is excess lactate production and a buildup of acid. It is often seen in serious illness, reduced perfusion, seizures, or substantial metabolic stress. If the patient is also hyperventilating, a respiratory alkalosis may coexist and make the pH less obviously abnormal.
Ketoacidosis happens when ketone production rises, most often in poorly controlled diabetes, prolonged fasting, or metabolic stress related to alcohol. The ketoacids raise the anion gap and lower bicarbonate. If the person is ventilating quickly from pain, anxiety, infection, or sepsis, the blood gas may show a second disorder on top of the acidosis.
Renal failure can also result in retention of acids that are normally removed by the kidneys. As kidney function worsens, unseen acids accumulate and the serum anion gap may go up. This can happen gradually or acutely, and it often requires close attention to electrolyte patterns and the full serum chemistry profile.
Recognizing Mixed Disorders in Lab Results
The key to recognizing a mixed acid-base disorder is not just noticing an abnormal number. You need to interpret the arterial blood gas, including pH and pCO2, together with the chemistry panel. Together, these values indicate whether the body’s response is expected or whether two separate processes are happening simultaneously.
You may see a low pH with low bicarbonate, which fits metabolic acidosis. But if the pCO2 is lower than expected, there may also be respiratory alkalosis. That is why the idea of a mixed disorder becomes important. The pH alone may not reveal the full story, especially if compensation is masking one component.
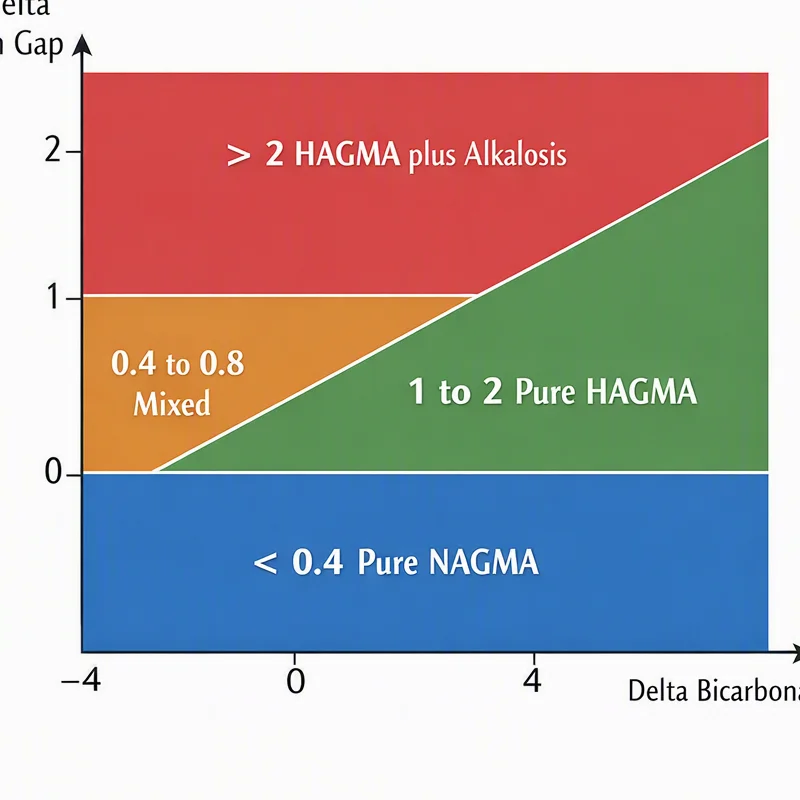
The delta gap is an additional helpful concept. It compares the rise in anion gap with the fall in bicarbonate. If the changes do not match expected patterns, a mixed process may be present. For example, a very high anion gap with only mild bicarbonate reduction may suggest an additional metabolic alkalosis. Likewise, an unexpectedly low pCO2 may point to superimposed respiratory alkalosis rather than simple compensation.
In practical terms, abnormal labs should raise questions like: Is the pH acidemic or alkalemic? Is the pCO2 moving in the direction you would expect? Does the anion gap fit the degree of bicarbonate loss? This approach helps identify a straightforward pattern from a more complex metabolic disturbance.
Step-by-Step Process to Understanding Results
A structured approach makes interpretation much easier. To begin, examine the pH to determine whether the patient is too acidic, alkalotic, or approximately normal. Then, determine whether the primary process appears of metabolic origin or respiratory. Then, review the serum anion gap to see whether there is evidence of elevated anion gap metabolic acidosis. This sequence offers a useful starting point for laboratory interpretation.
Then, use Winter's formula to predict the expected respiratory compensation for metabolic acidosis. If the measured pCO2 is well above than expected, there may be an additional respiratory acidosis. If the pCO2 is significantly lower than expected, respiratory alkalosis may be present. This remains one of the crucial steps in detecting a mixed acid-base disorder.
In the end, assess whether the observed pattern fits the expected physiology. True compensation is the body’s https://anion-gap-reference850.image-perth.org/anion-gap-calculator-for-detecting-occult-metabolic-acidosis expected response to a primary disorder, but compensation has constraints. When the blood gas does not match the expected pattern, it implies more than one process. That is often the signal that the patient has an underlying cause requiring immediate attention.
A practical rule: if the anion gap is elevated and the pCO2 does not match the expected compensatory response, think past a single diagnosis and look for a second acid-base process.
Examples of Elevated Anion Gap Mixed Conditions
A typical example is a patient with sepsis who develops lactic acidosis. This infection drives poor tissue perfusion and lactate buildup, causing marked anion gap acidosis. At the same time, the patient may hyperventilate from fever, pain, or systemic stress, producing respiratory alkalosis. The blood gas can show a pH that is higher than expected because the two disorders partially offset each other.
Another case involves toxic alcohols. These substances can generate acids that raise the anion gap, leading to severe metabolic acidosis. If the patient is also breathing rapidly due to physiologic stress, agitation, or central nervous system effects, a mixed pattern may appear. The result is a dangerous diagnostic situation that requires prompt recognition.
Salicylate poisoning is a classic mixed disorder. It often causes respiratory alkalosis early because the toxic exposure stimulates the respiratory center. Later, a high anion gap metabolic acidosis develops as acid metabolites accumulate. The combination can produce a deceptively near-normal pH, which is why blood gas analysis and serum chemistry must be reviewed together.
These patterns show why laboratory interpretation matters. A patient can be severely ill even when one number seems only mildly abnormal. The anion gap formula, pH, pCO2, and clinical presentation all need to be interpreted together to identify the correct diagnosis.
When to Seek Immediate Healthcare Evaluation
Certain findings should prompt urgent clinical evaluation, notably when they present alongside an raised anion gap. Concerning lab values such as a markedly reduced bicarbonate, significantly abnormal pH, or extremely elevated serum anion gap may indicate a potentially fatal metabolic disturbance. These results need urgent clinical attention rather than routine follow-up.
Symptoms matter just as much as lab results. Altered mental status, confusion, severe weakness, rapid breathing, chest discomfort, or inability to stay awake can all signal a critical acid-base disorder. If the patient is not protecting the airway or cannot provide a reliable history, the urgency increases.
Shock is another significant warning sign. Poor perfusion can worsen lactic acidosis and rapidly destabilize the acid-base status. In that setting, the elevated anion gap may reflect a serious underlying cause such as sepsis, toxic ingestion, or organ failure. Immediate evaluation is needed because these conditions can progress quickly.

In short, a mixed acid-base disorder with a high anion gap is not something to ignore. It can represent a critical electrolyte disorder or systemic illness that needs prompt diagnosis and treatment.
Frequently Asked Questions
What is considered an elevated anion gap?
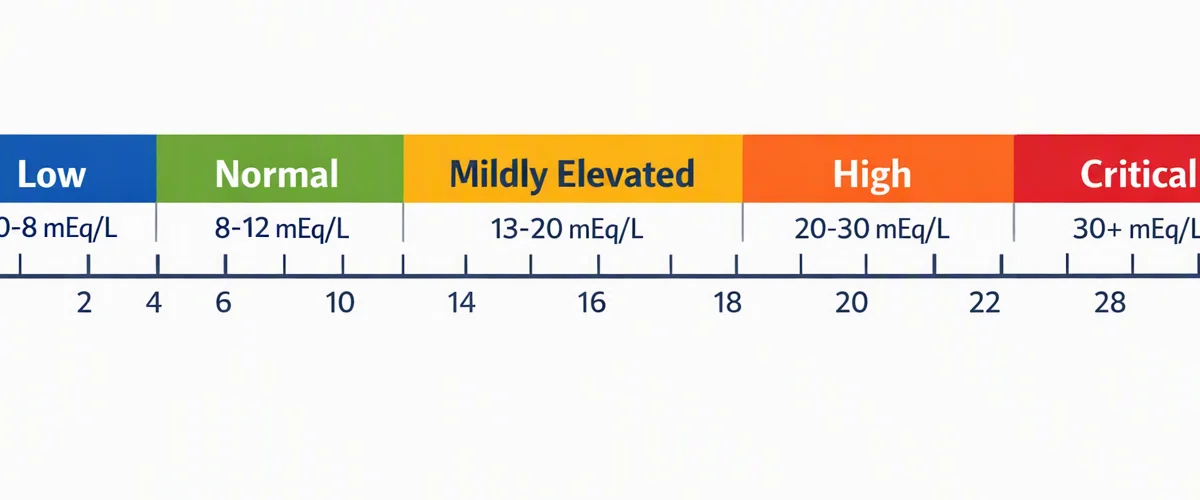
An elevated anion gap is a above-normal result on an anion gap calculation using serum sodium, serum chloride, and serum bicarbonate. The exact cutoff can vary by laboratory because reference ranges differ, but a clearly increased value suggests excess unmeasured anions and raises concern for high anion gap metabolic acidosis. Always interpret the number with the rest of the blood gas and serum chemistry results.
How does a mixed acid-base disorder differ from a simple disorder?
A simple disorder has one primary acid-base problem with an appropriate compensatory response. A mixed acid-base disorder has several separate processes happening at the same time, such as metabolic acidosis plus respiratory alkalosis. The clue is often that the pH, pCO2, and bicarbonate do not fit the expected pattern for a single disorder.
Can a patient have both metabolic acidosis and respiratory alkalosis at the same time?
Absolutely. This is a textbook mixed acid-base condition. It can happen in sepsis, salicylate poisoning, liver disease, or other situations where the body is making acid while also causing rapid breathing. In these cases, the pCO2 may be lower than expected for plain compensation, and the pH may appear less disturbed than the severity of illness would suggest.
What conditions most commonly cause a high anion gap?
Common causes include lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and salicylate poisoning. These conditions all generate or accumulate acids that increase the anion gap. The best differential diagnosis comes from combining the anion gap with the arterial blood gas, clinical findings, and other laboratory interpretation clues.
How do you calculate and interpret the anion gap in lab results?
The anion gap formula uses serum sodium minus the sum of serum chloride and serum bicarbonate. Anion Gap Calculator can speed up that process and reduce calculation errors. Once you have the result, compare it with the expected compensation using Winter's formula, review the pH and pCO2, and look for signs of a mixed disturbance. Interpretation works best when the calculated value is matched with the patient’s symptoms and underlying cause rather than viewed alone.